31 August 2006

Since when...?

Umm... when did Al Gore become cool? He was on the MTV Video Music Awards this year and he was better dressed, more articulate, and more passionate than during all of his campaign appearences put together. Not to mention his little documentary becoming a cult favourite among said MTV set. Even Bill Maher noticed - he said Al Gore had "found his voice" with this issue. Where was all this momentum when it mattered - during the election?

And speaking of Bill Maher... he's a republican?!

On the MTV subject, I wouldn't mind knowing which boyfriend turned Beyonce from an "independent woman" to a woman who will "cater to U". She went from buying her own cars to fetching his slippers. I realise than feminism is all about choice, but come on.

Lastly, when did it become fall? Don't get me wrong, I love the cooler crisp air, the warm cuddly sweaters and the clothes that hide a few more flaws than tank tops and mini skirts, but what happened to the summer? I distictly recall waking up each day thinking the season was dragging on but suddenly I realise that it went by deceptively quickly. All the undergrads have arrived on campus again bringing bustle and life back. Shops are extending their hours and CVS has devoted two isles to binders, mechanical pencils, and loose leaf. And I'm excited. One last fling of a weekend (back to NYC again - US Open tickets!) and it's buckle-down time: work is running smoothly and my brain is gearing up for the excitement (and I'm not being sarcastic) of microbiology and organic chemistry. I love the fall!


27 August 2006

2 year-itis

Freshly exhausted from a mini-vacation to New York City, I draped myself on the sofa, switched on James Bond in the background, and settled in to read my neglected email. Somewhere between my gmail and my yahoo account it struck me: two years seems to be the statute of limitation on your first post-collegiate job. Almost every mail shooting through cyberspace seems to bear news of a company change, an acceptance back to school, or a much yearned for interview. What is it that we (and I mean the collective, early twenties "we") are looking for? Are our expectations of the "real" world that far off the mark? Are our attention spans that short? Are we so undervalued or undertrained? Why are we able to commit to relationships, cities, and dreams, but not to our jobs?

I must admit to being a particularly early mover. I left my job in finance after a paltry 15 months and chose instead to backpack and scuba dive my time away before returning to school. In retrospect, my expectations were horribly unrealistic. And yet, what I wanted was nothing particularly grand: to be respected for the work I did, and to feel engaged and active in the process. It is the second half that led me to quit so quickly. After four years of maxing out my brain, it was suddenly switched off and that was more depressing to me than a six day work week and a two and a half hour commute.

As a result, I've now committed to the field in which you are a permanent student: medicine. It also happens to be the longest road to travel. Law school is three years, an MBA is two. A PhD is five, but I will be 30 when I get my MD and will still have my residency before I can prescribe meds without a guarantor (so to speak). I sincerely hope that it's not commitment phobia that makes us all change our minds so soon after school because the last seven months have shown me that medicine is exactly what I want to do. I am thinner, happier, and dare I say it, even a little more grown up.

Interestingly, most of the other post-bacs here are concerned over their ability to become physicians. While I have my moments of doubt (especially about the MCATs), I far more concerned over my ability to follow through than to pass organic chemistry. My worst fear is not rejection from medical school, it's inability to commit to a path. To accept reality for what it is, rather than what I want it to be.

15 August 2006

Before I die

I keep a book of things I want to do before I expire. It's not a morbid book. It's meant to remind me of the fun things I dream about and encourage me to take new adventures. I glue in pictures of the things I want to do and then glue in photos of things I've done. There's also a world map in the back with dots on every place I've traveled to.

Now, I'll come back to my book in a moment, but did you know how many esoteric lists of things to do before death are out there on the web? A few of the more unusual ones...

300 Beers to try before you die
50 Things to eat before you die
20 Hamburgers you must eat before you die
50 Places to flyfish before you die
5 Sentences Before you Die
101 Sex Tricks to try Before you die

So what's on my list? Here's a little sample of what I haven't done, but want to:

Be published nationally, own a dog, own Wellies, own a horse, work abroad, get a graduate degree, ride in a glider, be a teacher, own real artwork, ride in a helicopter, visit India, have my own library, get a motorcycle license, see penguins.

And what have I already managed?

Ride in a hot air balloon, see a solar eclipse, see an amazing band in concert, own superhero underwear, go scuba diving, go skydiving, visit Australia, visit Thailand, visit Russia, fly in the Concorde.

14 August 2006

And now for something completely different...

Finals are done and fall term doesn't begin until August the seventh. Accordingly, I find myself with all kinds of free-time on nights and weekends (recall, I now work full time in neurology) and anyone who knows me knows I get a teensy bit stir-crazy with free-time. In an effort to stave off relaxation-induced madness I've been exploring and I thought I'd show you some oddities from about town.

First, there was this sign outside a church. Apparently they are running out of ways to attract new parishioners and have resorted to a) declaring themselves cool, which any actually cool person/thing/activity would never have to do and b) advertising the presence of air-conditioning.


Then, there was the man with the pigeons all over him. Why would anyone want pigeons all over them and why is he wearing a suit when it's a million degrees out?


Inspired by the heat and for lack of an appropriate beach, there was this gem: a sandcastle being built on the sidewalk near the University.


And lastly, you know you're in a college town when the supermarket stocks up on back-to-school pong balls.

01 August 2006

Disclaimer!

Identifying information of persons mentioned in the blog have been altered to protect their privacy. This includes, but is not limited to, age, gender, race, date of visit, date of death, etc.

This blog is for entertainment only; please do not use it to diagnose or treat anything. I'm not an MD (yet) and may be wrong.

If you have questions or comments, feel free to comment on the blog posts or email me at webster.sm12@gmail.com.

Enjoy!

31 July 2006

Keeping Starbucks in business

For those of us lucky enough to be in summer classes, today is the first day of finals week. For those of you that have completed the collegiate phase of your life, you'll remeber this was the week you didn't get to drink. For me, this breaks down to: Neurochem tonight, Cellular Biology Wed night, Chem lab II Thurs morning and Clinical Research Thurs afternoon. Three days off... then my brand-spanking-super-fantastic new full-time job kicks off.

Because my brain is completely full and there's nothing I can write to make arcuate nucleus/paraventricular nucleus control over feeding behavior interesting to someone not already interested in neurochemisty... I thought it would be amusing to analyse the behaviors of post-bacs studying for finals.

# of libraries open on Sundays in University City: 1
# of post-bacs I spied from my one little chair in said library: 11
# of them who brought communal home-made gingersnaps: 1
# who bought snacks/lunch from Wawa: 11
# places besides wawa to get food in the vicinity: 0
# strange people with suitcases and smelly curry: 1 (not a post-bac)
# of med students in the medical library: 1
# undergrad TAs called into the library: 1
# cups of coffee consumed by post-bacs that day: lost count
# ice creams the girl I studied with ate: 2
# ice creams I ate: 0 (really!)
# text messages I sent while "studying": 23
# "quickies" I had between the stacks for stress relief: 0
# times I had sex that day/night for stress relief: none of your business ;)

Good luck everyone!

26 July 2006

Screwdriver + Chest = Pericardial Centesis

A day of teachable moments in the ER...

A patient was helicoptered into our ER from another ER (why is not exactly clear) with a stab wound to the left chest caused by a screwdriver. The patient had marked jugular distension (bulging neck veins), extreme hypotension (ie, no blood pressure), and muffled heart sounds. What does this (Beck's triad) of symptoms indicate? Cardiac tampenade!

The patient was bleeding into the sac around his heart (the pericardium) and this was putting pressure on the heart itself. Since there is no space around the heart, it cannot expand when filling with blood, limiting the volume of blood that can enter the ventricle. This means less blood is being pushed out with each contraction (decreased stroke volume and thus low blood pressure) and a build of of venous blood in the neck (think of a traffic jam in your superior vena cava).

To treat this particularly life threatening issue, the blood is drained from the pericardium while stabilizing the patient to get them to the OR. This draining procedure is the pericardial centesis and they performed it on the patient twice.

Had the patient been registering a blood pressure, we probably also would have seen pulsus paradoxus: a 10 point drop is systolic (top number- ventricular contraction) blood pressure on inhalation (breathing in). When you breathe in you are actually expanding your chest to create a highly negative pressure (4x less that the atmosphere) inside your lungs. This pulls air into your lungs (goes from high pressure to low) but it also helps pull thoracic blood (blood in your torso) back towards your heart. The thing is, if your heart can't expand because your chest is filled with blood, then filling the right side with venous blood leaves very little room on the right side for oxygenated blood coming from your lungs. Thus, even less blood is pushed out of the left side on contraction and you have an even lower blood pressure.

The trouble with working in the ER is that you don't "follow" your patients. He was alive when he got to the OR, I have no idea if he still is.

21 July 2006

Real Time Blogging from the ER

18:05 shift starts and all I have to start off with is three domestic violence screenings. In the process though I meet a very friendly third year med student.
18:30 checking the board for patients when a dr. comes and shows me a right wrist fracture on x-ray
19:30 finally consented a man for the cardiac study after trying to wake him for half an hour. Had to bang on the bed and even then he kept falling asleep in the middle of sentences. Chronic cocaine abuse, but seems to think quick highly of himself. Seems to think I would be fawning all over him if I'd met him in the hospital..hah!
19:50 dr. showed me cardiac man's EKG, unremarkable.
20:02 finally get to sit down for a minute to eat the food we ordered. Chicken kabobs with pita and tabolae salad.
20:25 processed cardiac man's bloods. Got 26 crio vials from the four tubes, takes about an hr to get through.
21:30 another round of domestic violence screenings to do...I've got seven so far, that's how many you generally get in a whole shift. This time I did one with the docs in the room on a 17 yr old pregnant girl. She's not the youngest pregnant I've seen either, record sits at 15.
21:41 Sophie whips out the MnMs - she's always got goodies :)
22:00 cardiac man is asking for even more juice (carton #6?) and is now claiming to be a singer/songwriter/politician/filmaker. Annoyed that dr won't give him Percocet so asking for a new dr. No doctor here will prescribe it (note in his file) so med student pretends to be a second opinion and denies him Percocet.
22:30 doing a domestic violence screening while playing swords with a woman's son. Apparently McDonalds now has inflatible swords for Pirates of the Carribean.
22:40 played patient advocate for some patients whose nurses had gotten busy; it's one of the side jobs, being able to help people by making sure they get the attention they need.
22:45 trauma alert went off for an incoming assault victim. ETA, less than 5 mins.
23:30 assault was pretty nasty - hit with bricks and planks by multiple assailants while trying to protect his father. Swollen and cut all over, still in his collar.
23:35 cardiac man is being transferred to a rehab facility because "to have a serious music career you really have to be clean. It's the Beatles, they brought all the drugs to the music. That's why they killed John Lennon, they were afraid people would follow him over the President."
23:55 wrapping up the paperwork and cleaning up the desk. Quick chat with the med students (they're pretty and have more time to be social). Should be out of here on time tonight, which will be a welcome change

07 July 2006

Nothing to do with medicene

Since so much of my (recently sparing) writing involves the hospital or class or some form of medical research, I thought I'd take a moment and reflect on the small corner of my life that is everything else (aka a life).

My parents trekked out here from LA to come and spent the fourth with me. I haven't seen them since last October, so the visit was welcome and singularly well-timed since I had just completed my midterms. They brought a heat wave with them, which was particularly tough on my mother when combined with the humidity so we needed some air-conditioned time. This was easily solved with a few boxes of hair dye - transforming me into a brunette became my mother's two-day project. We managed to find great seats for the fireworks, though we were less than impressed with the Lionel Richie concert (it's elevator, put-on-hold music). We also found the best Indian food this side of well, the globe, at Cafe Spice. Yum.

I have landed myself the coolest job ever as a clinical research associate in pediatric neurology where I'll be working on pediatric stroke and other cerebral vascular disorders. I'm really excited about it and with some luck and diligence I might be celebrating publication sometime in the next year and a half.

I've reached the six month mark with my "significant other" - a time span that simaltaneously feels like an era and a second. Next milestone, his birthday. Thankfully I have until September to think and rethink my gift selection.

My brother is off galavanting through Italy and my friends have all migrated (or are migrating to) California. I have been feeling the call of the West lately... though I shall have to put CA on hold until at least Christmas.

Right, I'm out of interesting tidbits... time to work/watch Netflix movies... fill in procrastinating activity here.

03 July 2006

MoyaMoya

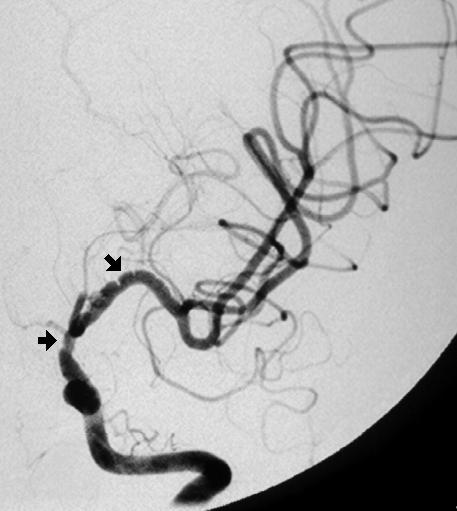
MoyaMoya is a cerebral vacular disease occuring most frequenting in Asian populations involving vascular occlusion (blockage) in the basal ganglia. On some occasions the brain grows many small vessels around the occlusion in an attempt to compensate for the decrease in blood flow, while other cases require cranial surgery.

This is one of the diseases I'm becomming familiar with now that I'm working in pediatric neurology research (yay!). The image below is from Hawaii and shows the occlusions fairly well. The image work I'm doing actually produces 4-D scans of the vascualture and allows us to calculate blood flow and velocity to different regions of the brain.


On a different note, we had a 186kg woman in the ER the other day. That's 410lbs. That's substantial.

Bella the MG dog

When we covered Acetylcholine (Ach) in neurochem one of the disorders we discussed was myasthenia gravis (MG). MG is an autoimmune disorder in which your body produces antibodies that block the Ach receptors of the neuromuscular junction. What this means is that when a nerve cell releases Ach to initiate muscle contraction, the muscle cannot receive the signal. The most prominant symptom of the disease is catalepsy (the inability to initiate voluntary movement).

The video (click here) shows Bella, a small dog, who has MG. Initially she cannot stand up and when the vet administers a blink test, she shows no reaction. The vet gives Bella some Edrophonium chloride, a drug that temporarily increases Ach tone. Subsequently, Bella can be seen running and reacting to the blink test until the medication wears off (it's called a Tensilon test). Bella is now on Pyridostigmine, a longer acting drug that also increases Ach tone, and has 75% of a normal dog's ability.

18 June 2006

Bottom of the ladder

Being a pre-med, post bac otherwise, is about as far down the proverbial ladder as you can find yourself. You are highly motivated to do something, but qualified to do nothing. The goal, when in the hospital, is to stay busy. Maybe even be useful occasionally. And to try not to be demoralised by the looks you get when you inevitably reveal that no, you're not a doctor and no, you can't treat [insert condition here]. It's the coats and ID badges, it confuses people.

A recent shift made all this very clear to me. For the first three hours nothing much was happening (in the post-surgery ward), but we were down two staff members, making those people with qualifications a tad overworked. That meant all the "comfort" care-taking fell to me and I was excited. I was busy. Really busy. Fetching juice, water, ice, gowns, blankets, paperwork for admits, answering phones, etc. Then it started, the after-dinner potty rush. None of the RNs or CNAs had time for this, so I spent my night rushing around putting people on the potty and into bed and cleaning up after the process. What's interesting is how thrilled I was to be doing this: it's about as close to doing something actually medically useful as I'll ever get before entering med school.

The it happened. Respitatory distress. A patient's O2 sat was in the 70s and not rising. Everyone was crowding into the room trying something. I was paging respiratory and medicene. Then came the discovery that we didn't have a continuous pulse ox, so I was calling every floor near us to borrow one. When I brought it back, the resp guys were there (the medicene consult would take another 40 minutes) and they let me stay in the room while they did their assesment (the family was kicked out). The patient had had a tracheotomy but was accumulating fluid and had to be constantly suctioned. Medicene came and did their own exam. We found our pulse ox. When I got back from returned the borrowed one, the Ear Nose and Throat (ENT) team was there. And when I say team, I mean TEAM. They brought a small army, all in matching green scrubs and surgical hats. They ate all the cookies, they crossed their arms and looked stern. They bantered with the medicene guys, but in the end, they didn't actually do anything as far as I can tell. The patient was to be moved to the SICU or MICU (intensive care units) where there are more monitors and more RNs/MDs per patient. Patient's O2 sat was climbing slowly. Crisis averted.

Time to put the remaining patients to bed and answer all the lights that had been ignored for the last 80 minutes. I go to help one of my favourite patients, we'll call him Dr. Doolittle, to discover that the charge nurse had kindly brought him a tape player and a book on tape over the last week. She brought him the New Testament on tape. He's Jewish.

06 June 2006

It's the thought that counts...

... and I had a lot of blog pieces floating around my head, but none of them seemed to make it out into cyberspace. Maybe I was too busy studying my chemisty and cell biology (exams today and tomorrow) or maybe I was too busy indulging in birthday fun (yes, I'm 24 now), but most likely I was just too busy living my life to write about it.

So, instead, the highlights...

There was a patient in the ER with a 108 degree fever suffering from heat stoke, I had my first positive domestic violence screening, a man with a cable through his eye, a boy whose father brought him in after beating him, a 28 year old boy rejecting his second stem cell transplant for Hodgkin's lymphoma, and my first baby ultrasound.

I had a whole post planned on the new Treasury secretary, former Goldman Sachs CEO Henry M Paulson, and how his new job is nothing more than PR. I was intending to put the short version here, but it's still a good post so maybe I'll still write that one. It will just be a tad less timely.

26 May 2006

Rough day in the ER

Last night I got my first taste of the thick skin I assume to you need to survive medical school and life in a hospital. It's emotionally tumultuous and on a bad day it's hard to remember that (hopefully) in the end you do more good than bad.
Before my shift we had a 4 hour orientation to the research studies going on in the ER at the moment. Three of them we were already trained on, so it was a complete waste of everyone's time. The fourth was announced as a go-live today, so basically myself and the other associate on duty were expected to march into the ER with the (unedited) forms and just start enrolling. It wouldn't have been a problem if the forms had been designed for a hospital site (as opposed to outpatient clinic) and the PI knew that cardiac patients (her most interesting population) were off-limits because the coronary studies would get priority.
Confusing and draining.
Ok, so paperwork isn't that bad and it can all be figured out. And you can catch up when the board is messy, even if you do feel a little disorganised. And you can eat enough graham crackers to stop feeling like you're going to keel over. But what's rough is when your patients keep telling you they don't want to talk to you, or enrolling and then withdrawing... or the nurse loses/throws out the blood you need.
Frustrating.
But then you lose a patient because they walk out of the ER against medical advice and your standing there with the EKG and you know that person really shouldn't have left. Or you do a domestic violence screening and the woman breaks down and tells you all about her monster of a husband and how she's trying to divorce him, but he's lying to the courts about her. Or your neurocog patient who doesn't finish the tests because they are in head CT and on their way up for neurosurgery. Or the kid who fell off his bike and can't stop crying because he can't remember anything. He looks at his hands if they're unfamiliar and his face is splotched with the bright pink of skin that's been torn off.
Heartbreaking.
Just as your finishing all the paperwork and spinning last bloods two doctors come up to you. One gives you a lecture on not approaching the patients too early and potentially causing double sticks. The other looks at your forms and says "What are you still doing here? What? What... you want extra credit or something for staying late?" No. No, I don't. I just want you to fill out the damn form so I can go home.
Maddening.
The next morning you wake up and find an email waiting for you... be sure to approach the patients early so as to get the bloods you need... copied to the whole damn world.
And we're back to frustrating.

Despite the whining... I love it there. Thursday nights are the best part of my week. If I could stay until 2:30 am every week, I would.

24 May 2006

Bowel Programs

This week on the surgical rehab floor I learned a little about bowel programs, something you've probably not thought of if you've never spent time in a hospital. The nurses spend a fair amount of time monitoring how often and how much you urinate and empty your bowels. There are even special chairs for this. Nice white plastic contraptions.
Almost as soon as I arrived for my shift a nurse called me into a patient room and asked if I would sit with the patient while he moved his bowels as it was taking some time and he had meds to attend too. So I sat there on the bed and tried, really tried, to have a conversation with this (not so lucid) patient between his gripping the chair sides and squeezing his eyes shut... wow, he kept saying, oh wow.
When the nurse returned I was informed the patient was severely impacted and had just been administered a supository (a butt pill). Apparently this wasn't sufficient because despite the groaning nothing was actually leaving patient's colon. Out came the maximum strength enema and another 20 minutes of sitting. Nothing.
At this point the nurse gave the patient a shower and decided to just put a diaper on him and call it a night. Problem is, the patient can't stand unaided, so I was recruited to pull the diaper up over his butt while the nurse held him up. It was this moment that the patient experienced some anal leakage (and bleeding). Nevertheless the patient was transferred to bed and the nurse and I cleaned up.
About an hour later the patient was caught trying to get out of bed (a no no since he can't walk). When questioned what he needed he expressed the need to "take a crap." The nurse was called in and the patient examined, but he was still unable to expell the impacted feces. At this point the nurse asked me to fetch some lubricant (can anyone guess where this is going?) which I brought back with some extra pairs of gloves. The nurse then proceeded to lubricate the rectum of the patient and break up the large, very solid mass lodged in his colon. Thankfully I was called out of the room by the other nurse on duty...
... only to find I had been called to another bowl issue. the first patient's neighbor was experiencing an unexpected bowl movement and needed to be placed on his toilet and washed (a process I assisted more than carried out since I am not a nurse). When I took the used toilet to be disposed and cleaned I saw what looked like a large orange hairball inside. This of course had to be brought to the nurse's attention.
By the end of the shift all bowels had been sucessfully moved and the smell on the ward confirmed it. As did the stack of brown gloves in the trash. Eew.

21 May 2006

Tagged again: oddities

Tagged and I'm it. Apparently the idea is to mention 6 odd things about yourself so here we go, six strange things you (probably) don't know about me:

1. I change into my pajamas when I'm at home, even if it's the middle of the day. It's a habit from a college roommate, but seriously, what's more comfy than PJ's?

2. I'd rather buy books than borrow them from a library; I just like owning them.

3. I'll put things into my agenda even after they've happened. That way I can look back and recall the night I went spontaneously went to drinks with so and so was Wednesday, not Thursday, for example.

4. I don't like ice cream cones. Give me a cup anyday. Or better, yet, the carton.

5. I sing in my car, when I'm alone. The top-of-my lungs, Carnegie Hall performance kind of singing, even though I couldn't carry a tune if you put a gun to my head.

6. I find it incredibly uncomfortable and nearly impossible to sit properly in a chair. I need to have one leg folded under me, be crosslegged, something.

16 hours in the hospital: week 1

And we have come to the end of the first week of summer session: all 4 classes, two tutoring shifts, and 16 hours in the hospital. And it was fun! I'm not being sarcastic here, I've definately taken on too much (par for the course) and I simply won't drop anything because I can't bear to give any of it up. Some highlights...
- In NeuroChem when the professor went over the finer points of cocaine delivery via snorting vs. freebasing and the resulting bioavailability curves.
- In Chem lab when the professor spent 20 minutes belittling post bacs and then mentioned that we'd likely have the highest grades in the class by the end.
- In tutoring (my job) when one of the students (veterans) told the head of the program I was inspiring and he wanted me to be his math teacher.
- In the post-surgery rehab ward when I had to take a patient (in a wheelchair) down to the front to smoke. Do you have any idea the looks you get when you ask a stranger for a lighter for the old man in the gown in the wheelchair while wearing a hospital ID and jacket?
- Realising I cannot get consistant readings on an electronic scale. Seriously, how did my crucible spontaneouly lose 2g?
- Watching the Emergency Room doctors treat a quadruple gunshot victim and then being sent to pick up their chinese food.
- Showing up to cell bio/biochem and realising everyone (practically) I know is in the class... and that it's moving to the coldest room on campus. I'm going to be wearing wool sweaters every Wednesday in the Philly humidity to avoid hypothermia.
- Having friends over Friday night for a cozy dinner and being able to congratulate Audra on getting into GW... way to go chica!
- Two lazy weekend mornings. Sleeping in, eating pancakes...
- Making to the movies... MI III is entertaining, Da Vinci code not so much.

11 May 2006

Inpatient Post-Surgery

It was my first night on the ward I am volunteering on in the hosptial and to my surprise, I actually managed to remember the CNA, RN, etc names! The patients were really interesting, some of them have been there for quite some time and I don't think there was a single one under the age of 50. A couple of guys in one room were rooting for opposing teams in the basketball team, which made for some fun conversations and light hearted smack talking. A woman with a leg injury was hell bent on seeing the baseball game (Mets -Philles) but it wasn't on any channels in the hosptial so we went searching everywhere for a radio.. more fun that it probably sounds.

On the unusual side there was a woman in a helmet whose brain was exposed. She had an edema and they couldn't close the wound (thus the helmet). She was rather large and immobile too so it made everything from changing into fresh gowns to serving dinner and changing bedpans a challenge. There was the 70 year old man with a penile implant... who couldn't keep it in his gown! and the man with a colostomy bag... we had to change it, well ok, the CNA had to change it, and it ended up spurting everywhere! Ick... guess who got to help clean ; )

Between Spring and Summer

Monday brings the beginning of summer classes and my job, both of which are exciting, but the 12 days in between have been really relaxing. First I had orientation for my job and it was one of the more inspiring few hours I've ever witnessed. I tutor veterans who want to try and go to college and one of them talked about how he wanted this so his kids would be proud of their dad and would know that they could go to college too.

After orientation was Audra's BBQ, which was a fun and relaxing outdoor yumfest. Best moment, Taner scooping ice cream for us all :) Or maybe Abi, Taner's HUGE dog, farting in the car!


I spent a few days in NYC where I saw David Blaine underwater - he was living in a human fishbowl for eight days. I saw the Natural History Museum for the first time too... and recognised all the words laid into the marble floor: gnathosomes, tetrapods, amniotes...


Back in Philly was a fun trip to Ikea to pick up furniture... I'm still a little weirded out by owning furniture. They had a big tub of blue balls to play in, which made everything better... that and the ice cream cones :)


And now... my fridge isn't working and I need to go and buy my textbooks. Yup, I smell summer session approaching.

29 April 2006

Bio Exam III and Final

I just took two exams; you get 10 questions. As per a reader's request, I will not post the answers in the comments, you can :)

Q1. What is anhydrobiosys?
Q2. What is parthenogenesis? (hint: check a previous post)
Q3. What is necessary for the activation of a cytotoxic T cell?
Q4. Name the three phases of the uterine cycle and the corresponding phases of the ovarian cycle.
Q5. What are Leydig cells and what stimulate them/ do they secrete?
Q6. Name, in order, the regions of the stomach, small intestine, large intestine and their sphincters.
Q7. What is the common name for Nematoda? Nemertea? Which is segmented?
Q8. Name one difference between bacteria and archea. Which is more closely related to eukaryotes?
Q9. Name, in order, the parts of a nephron.
Q10. What hormones does the adrenal medulla secrete? The adrenal cortex?

Extra Credit: Write the bicarb buffer equation.